


Have you ever found a wide QRS in the middle of atrial fibrillation and thought it was a premature ventricular contraction? Be careful: it may be the Ashman phenomenon, a classic pitfall every ECG reader needs to know.
In this post, we explain how to recognize the Ashman phenomenon, why it occurs and which criteria help differentiate it from premature ventricular beats.
A bit of history
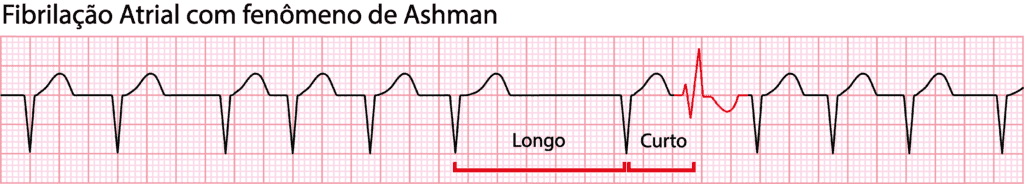
The phenomenon was described in 1947 by Gouaux and Ashman, who observed patients with atrial fibrillation. They noticed that, after a relatively long RR cycle followed by a short cycle, the next beat could show an aberrant morphology resembling right bundle branch block (RBBB).
This conduction aberrancy is not a fixed disorder of the conduction system, but a functional, transient phenomenon, driven by the behavior of the refractory period of the His-Purkinje system.
The pathophysiology behind the phenomenon
The mechanism is simple but elegant:
- A longer RR cycle allows greater recovery and, consequently, prolongs the refractory period of the bundle branches.
- If this long cycle is followed by a short cycle, the supraventricular impulse may reach the His-Purkinje system while one of the bundle branches is still refractory.
- The right bundle branch, which naturally has a longer refractory period, is the one most often involved, resulting in an RBBB morphology.
Electrocardiographic criteria for the Ashman phenomenon
✅ A long RR cycle immediately before an aberrant QRS (classic pattern: short–long–short)
✅ Wide QRS with bundle branch block morphology (usually RBBB, but it may vary)
✅ Normal orientation of the initial vector of the QRS (helps differentiate it from premature ventricular contractions)
✅ Variable coupling interval of the aberrant QRS complexes (not fixed as in premature beats)
✅ Absence of a compensatory pause, especially in atrial fibrillation
How to differentiate it from a premature ventricular contraction?
🔍 The Ashman phenomenon is supraventricular: the impulse originates in the atria, but ventricular conduction is aberrant for functional reasons.
A premature ventricular contraction, on the other hand:
- Occurs early
- Has a fixed coupling interval
- May be followed by a compensatory pause
- Usually has an abnormal initial vector (because it originates in the ventricle)
Recognizing these patterns helps avoid diagnostic errors and unnecessary interventions.
Conclusion
The Ashman phenomenon is a classic example of how careful analysis of RR cycles and QRS morphology can prevent confusion on the ECG. It is especially important in patients with atrial fibrillation, where the short–long–short pattern may mask wide-QRS beats that are not ventricular.
Stay alert: a wide QRS is not always a premature ventricular contraction!
References
- Scheffer MK, De Marchi MFN, de Alencar Neto JN, Felicioni SP. Eletrocardiograma de A a Z. São Paulo: Manole, 2024.
- Issa Z, Miller J, Zipes D. Clinical Arrhythmology and Electrophysiology: A Companion to Braunwald’s Heart Disease. 3rd ed. Philadelphia: Elsevier; 2019. 752 p.








